Thoughts on these points?It seems like they had quite a few. primary outcomes. Did they do any correcting for multiple tests? I didn't see it.
Also, can someone explain to me the difference between the ANCOVA findings on the primary outcomes, and the mixed models for repeated measures (MMRM) results? They seem to get different results on those for the PHQ-15 on somatic symptoms--there's no difference in the primary analysis but there is a difference in the MMRM analysis, which was part of sensitivity analysis but is what they mention in the abstract. Also, they refer to the MMRM results as "post-hoc," which I also don't understand.

- ME/CFS and Long Covid research
- ME/CFS and Long Covid research
- Psychosomatic research - ME/CFS and Long Covid
You are using an out of date browser. It may not display this or other websites correctly.
You should upgrade or use an alternative browser.
You should upgrade or use an alternative browser.
Cognitive-behavioral therapy for post COVID-19 condition: A pilot randomized controlled trial, 2026, Sauer et al.
- Thread starter SNT Gatchaman
- Start date

ME/CFS Science Blog
Senior Member (Voting Rights)
Anyone able to find the trial registration?The study was preregistered at the German Clinical Trials Register (DRKS000333476; registration date: February 1, 2024) a
Don't see it either and they mention 5 primary outcomes. With correction none would be statistically significant.It seems like they had quite a few. primary outcomes. Did they do any correcting for multiple tests? I didn't see it.
Post-hoc usually means that it wasn't pre-specified and decided after seeing the results.Also, can someone explain to me the difference between the ANCOVA findings on the primary outcomes, and the mixed models for repeated measures (MMRM) results? They seem to get different results on those for the PHQ-15 on somatic symptoms--there's no difference in the primary analysis but there is a difference in the MMRM analysis, which was part of sensitivity analysis but is what they mention in the abstract. Also, they refer to the MMRM results as "post-hoc," which I also don't understand.
Don't think the ANCOVA versus MMRM difference matters much but it does seem like they tried to get more significant results by using another statistical approach.

Nightsong
Senior Member (Voting Rights)
DRKS00033476 (DRKS.de)Anyone able to find the trial registration?

Utsikt
Senior Member (Voting Rights)
I’ve added line breaks and bolding:
Primary outcome:
Intensity of body complaints (incl. fatigue, breathing difficulties, circulatory problems, Post-Exertion-Symptoms) with Patient Health Questionnaire - 15 (PHQ-15),
Fatigue Severity Scale (FSS),
Scales "Breathing" and "Circulation" of the Symptom Burden Questionnaire - Long Covid (SBQ-LC),
Scale "Post-Exertion Malaise" of the DePaul Symptom Questionnaire-2 at T0, T1, T2, T3;
Symptom-related thoughts, feelings, and behaviors (symptom burden) with Somatic Symptom Disorder B - Criteria Scale (SSD-12) at T0, T1, T2, T3;
Session rating with Session Rating Scale (SRS) and Group Therapy Session Evaluation form-P/T (GTS-P/T) after each single and group session;
Side effects of treatment with Inventory for the balanced assessment of Negative Effects of Psychotherapy (INEP) at T1 or T2
I don’t think they understand what primary means. You’re supposed to pick one, and that’s the one you do the power calculations for.Secondary outcome:
Disease coping with Brief Illness Perception Questionnaire (B-IPQ) at T0, T1, T2, T3;
Somatosensory Amplification with Somatosensory Amplification Scale (SSAS) at T0, T1, T2, T3;
Construkts of the somatoform spectrum of the Hierarchical Taxonomy of Psychopathology (HiTOP) with short-scale for the somatoform spectrum of the HiTOP zu T0, T1, T2, T3;
Treatment expectations with Credibility/Expectancy Questionnaire (CEQ) at T0;
Anxiety Symptoms with Generalized Anxiety Disorder Scale-7 (GAD-7) at T0, T1, T2, T3;
Depressive Symptoms with Patient Health Questionnaire-9 (PHQ-9) at T0, T1, T2, T3;
Impairments of work productivity and activity with Work Productivity and Activity Impairment Questionnaire (WPAI) at T0, T1, T2, T3
Post-hoc usually means that it wasn't pre-specified and decided after seeing the results.
Don't think the ANCOVA versus MMRM difference matters much but it does seem like they tried to get more significant results by using another statistical approach.
I was confused about why they called it "post-hoc" because they mentioned the MMRM analysis in their statistical plan without saying it was post-hoc, so I assumed it was part of the overall plan.
As far as the two analyses, I was interested in what the different meanings would be of the two different analyses. They present the MMRM analysis of the PHQ-15 as part of the conclusion in the abstract even though I guess it's not the actual primary analysis. What is its status? It uses the primary outcome data but for a different analysis. So it's a seocndary analysis of the primary outcome results, I guess?

JellyBabyKid
Senior Member (Voting Rights)
For goodness sake, don't give them any more ideasMight as well ask how beige a sound is, or how much roundness defines the saltiness of a piece of food

I reckon this study would be a gold mine of dross if someone wanted to take the time to dig into it. The error bars on the chart are Standard Error. The use of SE in charts seems to be a nearly 100% reliable measure of a bad study.More from the unblinded intervention / subjective outcomes brigade. Credit for not amputating the y-axis but apparently "this pilot RCT indicates that CBT can lead to improvements in fatigue in individuals with PCC, even among those who are severely impaired and show high rates of PEM."
The improvement:

The standard deviations of the Fatigue measure at baseline were 0.70 for the CBT group and 0.81 for the waitlist group (from Table 1). Imagine SD error bars of 0.8 either side of the mean points. (Why report SD in the table but use SE on the chart?)
The differences between treatment groups are ridiculously inconsequential. And that's before we start to take into account the fact that the result is a subjective report, influenced by expectation, and particularly influenced when the intervention aims to change how symptoms are interpreted.
..................CBT.....................................................................Waitlist........................
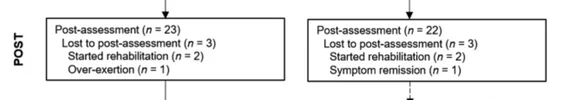
And look at that from the waterfall chart. CBT on the left, waitlist on the right. In the CBT group, one person is reported to have dropped out because of "over-exertion", and so their results did not contribute to the post-treatment means. In the waitlist group, one person is reported to have dropped out because of "symptom remission", and so their results did not contribute to the post-treatment means!
Seriously! in small cohorts, just over 20, they excluded a person who presumably had massively increased fatigue from the CBT group and excluded a person who clearly had a major reduction in fatigue (possibly to normal levels) from the waitlist group. Those decisions alone probably are enough to completely change the between group mean differences at treatment end.
This looks to be a really bad study. How dare they suggest that it indicates that CBT has been shown to have "preliminary efficacy"?
Last edited:
The differences between treatment groups
I couldn't really tell from the table what the numerical difference between the groups was on the FSS, although it looks very small on the chart. Also, I wonder if the purported benefit met the minimal clnically important difference for the FSS.
ME/CFS Science Blog
Senior Member (Voting Rights)
Not sure, but I suspect it would be bigger because the standardized effect size was a Cohen's d of 0.56. That is usually larger than the minimal clinically important difference.wonder if the purported benefit met the minimal clnically important difference for the FSS.
Think the biggest problems of this trial lie elsewhere: no control condition, no objective outcomes, no correction for multiple comparisons, etc. It feels more like a promo article for CBT than a study that actually contributes to the scientific literature.

They're nearly always open access, which I'd assumed reflected the available funding and cheap-to-run studies. (I've updated the initial post.)By the way, the study isn't paywalled now.
That Journal of Psychosomatic Research is such a compendium of bad science. Have we ever seen a decent study in it?
The efficacy of exercise in patients with myalgic encephalomyelitis/chronic fatigue syndrome: A systematic review and meta-analysis (2026)
Treatment effects of multimodal inpatient psychotherapy for post-COVID patients: First results from a non-randomized, controlled study (2026)
Exercise interventions for physical function, psychological health, and quality of life in patients with myalgic encephalomyelitis/chronic fatigue syndrome and fibromyalgia: A systematic review and network meta-analysis (2026)
The association of fatigue and pain with cognitive test performance in patients with myalgic encephalomyelitis/chronic fatigue syndrome (2025)
Different patterns of persistent somatic symptoms after COVID-19 reported by the Dutch media and the general population (2024)
Factors associated with having previously received a diagnosis of fibromyalgia, chronic fatigue syndrome and irritable bowel syndrome: A cross sectional DanFunD study (2024)
all had at least some reasonable aspects or discussion points.
Fair enough. Although 'having at least some reasonable aspects' is a fairly low bar.all had at least some reasonable aspects or discussion points.
I note, for example one comment on the forum about the second paper on the list was
To actually announce that your study is non-randomised, as well as omitting that it is non-blinded and pretending it is effectively controlled seems like scraping the floor of the cellar under the barrel.
ME/CFS Science Blog
Senior Member (Voting Rights)
Someone has looked into it on Twitter:Not sure, but I suspect it would be bigger because the standardized effect size was a Cohen's d of 0.56. That is usually larger than the minimal clinically important difference.
you mean in terms of standard deviations?Not sure, but I suspect it would be bigger because the standardized effect size was a Cohen's d of 0.56. That is usually larger than the minimal clinically important difference.
ME/CFS Science Blog
Senior Member (Voting Rights)
Yesyou mean in terms of standard deviations?
Trial By Error: Yet Another CBT Trial for Long Covid with Poor Results | Virology Blog
By David Tuller, DrPH The Journal of Psychosomatic Research has often served as a house organ of sorts for the “biopsychosocial” ideological brigades. That’ ...
 virology.ws
Very nice, thanks David.
small typo:
There's also the issue of the dropouts, with the person who over-exerted being excluded from the CBT group (likely their fatigue went way up) and the person who had symptom remission being excluded from the waitlist group (likely their fatigue went way down). When the numbers of participants are small, and the difference between the two groups is very small, the impact of those "dropouts" probably matters.
I'm actually surprised the authors were so upfront about the reasons why people were excluded. Normally we see dropouts explained away in ways that don't make it clear that symptom exacerbation as a result of over-exertion is a possible outcome when in the CBT group. Nor that hanging around on the waitlist group can cure someone.
In fact, I reckon if I had the trial data, and got estimates of the post-treatment fatigue ratings for those two dropout people and included them, ... maybe tweaked a few of the other assumptions, I could report in good conscience that "the pilot trial suggests that the feasibility and preliminary efficacy of "waitlist" treatment for PCC". Hell, it even cured someone and didn't mess with people's minds! And, it's very cheap.
small typo:
Right after treatment, besides the marginal benefit for the intervention arm on fatigue, there was a benefit on a breathing measure right that also disappeared at follow-up.
There's also the issue of the dropouts, with the person who over-exerted being excluded from the CBT group (likely their fatigue went way up) and the person who had symptom remission being excluded from the waitlist group (likely their fatigue went way down). When the numbers of participants are small, and the difference between the two groups is very small, the impact of those "dropouts" probably matters.
I'm actually surprised the authors were so upfront about the reasons why people were excluded. Normally we see dropouts explained away in ways that don't make it clear that symptom exacerbation as a result of over-exertion is a possible outcome when in the CBT group. Nor that hanging around on the waitlist group can cure someone.
In fact, I reckon if I had the trial data, and got estimates of the post-treatment fatigue ratings for those two dropout people and included them, ... maybe tweaked a few of the other assumptions, I could report in good conscience that "the pilot trial suggests that the feasibility and preliminary efficacy of "waitlist" treatment for PCC". Hell, it even cured someone and didn't mess with people's minds! And, it's very cheap.
Anyone know what LP screening questions are like ?[59] is Psychometric properties of the credibility/expectancy questionnaire (2000)
That questionnaire is —
"We would like you to indicate below how much you believe, right now, that the therapy you are receiving will help to reduce your anxiety. Belief usually has two aspects to it: (1) what one thinks will happen and (2) what one feels will happen. Sometimes these are similar; sometimes they are di!erent. Please answer the questions below. In the "first set, answer in terms of what you think. In the second set answer in terms of what you really and truly feel. We do not want your therapist to ever see these ratings, so please keep the sheet covered when you are done."
Set I
Set II
- At this point, how logical does the therapy offered to you seem?
- At this point, how successfully do you think this treatment will be in reducing your trauma symptoms?
- How confident would you be in recommending this treatment to a friend who experiences similar problems?
- By the end of the therapy period, how much improvement in your trauma symptoms do you think will occur?
For this set, close your eyes for a few moments, and try to identify what you really feel about the therapy and its likely success. Then answer the following questions.
- At this point, how much do you really feel that therapy will help you to reduce your trauma symptoms?
- By the end of the therapy period, how much improvement in your trauma symptoms do you really feel will occur?
View attachment 33230
According to that the CBT and Waitlist Controls had similar assessment of the credibility and expectation for their respective treatments prior to. Eg credibility was 7.76±1.18 for CBT and 7.28±0.89 for WLC.
TBM (Truthiness-Based Medicine) I guess.
I wouldn't be surprised if they were spookily similar - now entering " mainstream" research.
A quote from a recent study on possible harm from psychotherapy seems relevant here:
Iatrogenic Harm, Psychotherapy, and Eating Disorders: An Urgent Call to Action 2026 Cobbaert
To exclude a patient's results from the CBT treatment group because of 'over-exertion' is clear patient-blaming, and serves to inflate perceptions of treatment safety and effectiveness. The authors don't seem to realise that the failure is in a treatment that exhorts patients to push through; they have to take at least some of the blame for the deterioration.
Iatrogenic Harm, Psychotherapy, and Eating Disorders: An Urgent Call to Action 2026 Cobbaert
Treatment dropout and the attribution of treatment failure to patients are examined as mechanisms that obscure harm and inflate perceptions of treatment safety and effectiveness.
To exclude a patient's results from the CBT treatment group because of 'over-exertion' is clear patient-blaming, and serves to inflate perceptions of treatment safety and effectiveness. The authors don't seem to realise that the failure is in a treatment that exhorts patients to push through; they have to take at least some of the blame for the deterioration.
