I relapsed on SCIG. Haven’t gained back that function in two years since. Apparent treatment harms just don’t have the legs apparent improvements do.Which type of groups are you in ?
Seasoned ME patients ?
Would be interesting how you summarize their experience.
Personally, I know some patients that benefit / benefited and also some patients that have crashed from IVIG
From SCIG I haven’t heard any crash story as of yet.
……………
Currently wrt data - as far as I can recollect - there were a few (inconclusive) small ME patient IVIG trials quite some time ago, one recent on low dosage SCIG, and there is one trial for Long Covid coming up in the US.
And than there is anecdotal experiences and lowest quality of online survey data available.

You are using an out of date browser. It may not display this or other websites correctly.
You should upgrade or use an alternative browser.
You should upgrade or use an alternative browser.
neophyte32
Senior Member (Voting Rights)
I tried IVIG despite my severe condition. It was hard getting to the hospital, but I did it twice—first at 0.20 and then at 0.40 per kilo. There was no particular benefit.
I had my first at-home session three days ago—SCIG this time—at 0.25 per kilo (twice a month); I felt very unwell afterwards and the next day. I felt okay yesterday, but today I’m feeling bad again. I can tell because my baseline tachycardia is worse on the days I’m not doing well...
Yesterday, my heart rate was between 75 and 90 while standing (I’ve been on a low dose of nebivolol for a year), whereas today it’s 95–105...
I’m going to continue for another two months, but if things get worse in 10 days after second SCIVIG, I’ll stop... im bedridden but i can speak and use my Phone...
Last edited:
I found the sessions to be hard on my body as well. Administering the drug and sitting uncomfortably while it infused being part. But it also made my head feel very spacey in ways that made it hard to do much else on the day of.I tried IVIG despite my severe condition. It was hard getting to the hospital, but I did it twice—first at 0.20 and then at 0.40 per kilo. There was no particular benefit.
I had my first at-home session three days ago—SCIG this time—at 0.25 per kilo (twice a month); I felt very unwell afterwards and the next day. I felt okay yesterday, but today I’m feeling bad again. I can tell because my baseline tachycardia is worse on the days I’m not doing well...
Yesterday, my heart rate was between 75 and 90 while standing (I’ve been on a low dose of nebivolol for a year), whereas today it’s 95–105...
I’m going to continue for another two months, but if things get worse in 10 days after second SCIVIG, I’ll stop... im bedridden but i can speak and use my Phone...

fst
Senior Member (Voting Rights)
FWIW, being severe, I had an immuno absorption and 0.5 mg/kg IVIG. Obviously I can't tell which of these (if any) caused the effects.
I think it improved my PEM. After the whole endeavor I crashed for only 3 days (expecting multiple weeks). The PEM also felt less "bodily".
Also my heart rate got noticeably lower and my muscles stopped hurting for about 4 weeks.
What was left was debilitating fatigue and unchanged cognitive symptoms. Much like @ryanc97 said. Actually, I even felt more fatiqued than before, but I prefer it to being completely wired all the time.
Overall, it did not help or change my quality of life (or Bell Score) much, but it also did not hurt. Probably just a waste of money, but I felt that I had to try.
Last edited:

ryanc97
Senior Member (Voting Rights)
Yeah, I wish it helped w my fatigue.FWIW, being severe, I had an immuno absorption and 0.5 mg/kg IVIG. Obviously I can't tell which of these (if any) caused the effects.
I think it improved my PEM. After the whole endeavor I crashed for only 3 days (expecting multiple weeks). The PEM also felt less "bodily".
Also my heart rate got noticeably lower and my muscles stopped hurting for about 4 weeks.
What was left was debilitating fatigue and unchanged cognitive symptoms. Much like @ryanc97 said. Actually, I even felt more fatiqued than before, but I prefer it to being completely wired all the time.
Overall, it did not help or change my quality of life (or Bell Score) much, but it also did not hurt. Probably just a waste of money, but I felt that I had to try.
I would trade being in mild pain and pots and muscle twitching if I could get road off the fatigue.
But at the same time, both is too much to handle, so I’m lucky it helps me in one aspect
ryanc97
Senior Member (Voting Rights)
so @neophyte32 how is the IVIG treatment going?
neophyte32
Senior Member (Voting Rights)
Scivig sucks. IVIG is much better but too severe to go hospital every monthso @neophyte32 how is the IVIG treatment going?
Side effects : arthritis-like, body pain, diarrhea, fatigue...
Good effects : more strenght in muscle for few days, im sweating again and... that s all.
Ive stopped after 3 months at 0,55 per kilos. I have the choice to try again in september.
It s not a game changer, clearly not for me.
But i suspect my MECFS onset during my tramadol dependance... so more pharmacological (serotonin problems) than Covid... or maybe both. Anyway it s such a mess.

jnmaciuch
Senior Member (Voting Rights)
I just came from a presentation which strongly supports the idea that IVIG treatments may work in some diseases through specific glycosylation patterns on antibodies that affect Fc-receptor-bearing cells. It seems like circulating antibodies, regardless of their antigen specificity, have a regulatory capacity on myeloid activation through post-translational modications on both the head and stem (there was a paper showing that one specific modification strongly suppresses NFkB signaling in alveolar macrophages during infection). There's also this paper showing that pre-existing glycosylation levels on serum Ig is strongly predictive of response to IVIG in Kawasaki's disease.
Posting the idle thought in case any researchers are actually interested in rigorously pursuing the "subgroup of responders" idea--this is a legitimate hypothesis and something that can be assessed before initiating treatment.
Also, if there does turn out to be a legitimate subgroup of responders to IVIG that can be predicted by this mechanism, that would be very interesting for theorizing ME/CFS. Circulating immunoglobulins typically aren't crossing the blood brain barrier in high concentration, so it would indicate that whatever was driving disease in those responders is located outside the CNS.

Jonathan Edwards
Senior Member (Voting Rights)
I just came from a presentation which strongly supports the idea that IVIG treatments may work in some diseases through specific glycosylation patterns on antibodies that affect Fc-receptor-bearing cells.
Ig glycosylation patterns were all the rage in 1990. Well funded groups spent a decade or so exploring them, convinced that they were the key to both diagnosis and treatment. It all blew away like autumn leaves. I got interested initially but some old friends in biopharma pointed out the near impossibility of actually proving anything. Soon after, simpler ideas began to make sense.
jnmaciuch
Senior Member (Voting Rights)
Whats the near impossibility?I got interested initially but some old friends in biopharma pointed out the near impossibility of actually proving anything
I don’t think it’s the Rosetta Stone for anything. But I think it provides one legitimate hypothesis for the IVIG camp to actually look into, given the clear predictive indications in at least one immune-mediated disease. It seems like they intend to keep prescribing it and seek funding for trials anyways. Might as well suggest one measurement that has some chance of answering a sensible questionWell funded groups spent a decade or so exploring them, convinced that they were the key to both diagnosis and treatment.
Jonathan Edwards
Senior Member (Voting Rights)
Whats the near impossibility?
I think it boiled down to the combinatorial range of carbohydrate moiety options, the broad overlap of relative proportions of each in all situations known at the time, the combinatorial range of Ig species directed at any particular antigen and the problem of making any sense of it by looking at protein (with sugars) rather than RNA. The experiment I wanted to do may have been particularly impossible but all the headline-making claims about agalactosyl IgG in RA and 'glycosylation fingerprints' for dozens of other diseases quietly disappeared as people tried to replicate.
Jonathan Edwards
Senior Member (Voting Rights)
But I think it provides one legitimate hypothesis for the IVIG camp to actually look into, given the clear predictive indications in at least one immune-mediated disease.
But that was the glycosylation of the endogenous IgG was it not? That might be a marker of all sorts of other things. I think the basic observation that you get shifts in glycosylation patterns with active inflammatory disease held up. It just didn't explain anything it was supposed to.
I am pretty sure that we can assume that IVIg doesn't work. The enthusiasm for IVIg looks to me much the same as it was for things like Wegener's and myositis in the 1980s.
jnmaciuch
Senior Member (Voting Rights)
But it's not explaining disease state overall, it's explaining responsiveness to IVIG specifically in cases like Kawasaki's disease. If someone's inflammatory disease causes substantial loss of antibody glycosylation, then administering IVIG might work by reinstating an immunoregulatory mechanism. If someone already had normal levels of glycosylation on endogenous Ig, it just indicates that their specific disease state is driven by something beyond whatever antibody glycosylation can touch. So it makes sense that they wouldn't respond to more glycosylated antibody.But that was the glycosylation of the endogenous IgG was it not? That might be a marker of all sorts of other things. I think the basic observation that you get shifts in glycosylation patterns with active inflammatory disease held up. It just didn't explain anything it was supposed to.
It might just be only a small subset of cases for a disease like Kawasaki's that are in that low-endogenous-antibody-glycosylation disease state. All you would need to prove it in a new context is to use pre-treatment levels as recruitment criteria, give one group normal IVIG, and the other group IVIG pre-treated with a glycoprotein cleavage enzyme.
I'll give updates when the data from that discussion is finally published. Like I said, I don't think it's a Rosetta stone for all immune-mediated disease. But there are some pretty strong indications in particular contexts.I think it boiled down to the combinatorial range of carbohydrate moiety options, the broad overlap of relative proportions of each in all situations known at the time, the combinatorial range of Ig species directed at any particular antigen and the problem of making any sense of it by looking at protein (with sugars) rather than RNA.
Jonathan Edwards
Senior Member (Voting Rights)
But it's not explaining disease state overall, it's explaining responsiveness to IVIG specifically in cases like Kawasaki's disease. If someone's inflammatory disease causes substantial loss of antibody glycosylation, then administering IVIG might work by reinstating an immunoregulatory mechanism.
Yes, but that is so vague you might as well postulate any old stuff. As far as I know nobody has ever observed such a mechanism. People have been speculating about this sort of 'rebalancing regulation' with IVIg for decades. From what I know of B cell behaviour in disease it seems to me highly implausible.
And I bet there is no shift in glycosylation in ME/CFS.
jnmaciuch
Senior Member (Voting Rights)
Well I said “immunoregulatory mechanism” since it’s less work than repeatedly typing out “Fc receptor mediated induction of the transcription factor REST that suppresses NFkB signaling in myeloids associated with inflammatory damage in severe influenza and Kawasaki’s disease”Yes, but that is so vague you might as well postulate any old stuff. As far as I know nobody has ever observed such a mechanism.
It wouldn’t be on B cells, and my whole reason for commenting was to discuss recent mechanistic studies and hypothesesPeople have been speculating about this sort of 'rebalancing regulation' with IVIg for decades. From what I know of B cell behaviour in disease it seems to me highly implausible.
Probably not for the vast majority of people with ME/CFS. That wasnt my argument. I don’t think it’s worth my time to keep reiterating and spoonfeeding here when my words are getting swapped out for things some other people said in the 90sAnd I bet there is no shift in glycosylation in ME/CFS
Jonathan Edwards
Senior Member (Voting Rights)
Probably not for the vast majority of people with ME/CFS.
Hang on, isn't this just the sort of subset argument we have been getting tired of for a while?
The point of the 1990s arguments is that if you step back from one single step in a pathway and consider the plausibility in the wider dyanmic system, which will certainly include B cells, since we are talking about antibodies, it all becomes rather difficult to find a story that doesn't predict various aspects of disease that we haven't observed.
I appreciate the intention - to bring in a new speculation that we can toss around. I am all for that. But I spent so many years trying to get this sort of idea to work when colleagues were intoning it from high towers that I think it reasonable to express scepticism!!
Basically IVIg is feeble at best for pretty much anything. But that will not stop immunologists selling their theories about it, even if the data turns out to be the opposite of predicted. And this forum exists, arguably, because on another forum I was not allowed to say things like that without having posts deleted, and then some people seriously closed ranks.
jnmaciuch
Senior Member (Voting Rights)
Hang on, isn't this just the sort of subset argument we have been getting tired of for a while?
One more time, for old times' sake.
Given that:
1) research groups are already publicly planning trials for IVIG.
2) research groups are already chasing the idea of “subgroup biomarkers” regardless of whether people on this forum think that is worthwhile.
It might be interesting to:
1) conduct one measurement of baseline antibody glycosylation in these trials on the off-chance that it strongly predicts treatment response as it does in Kawasaki’s disease.
This is a good idea because:
1) funding is already going towards trialing IVIG whether we like it or not, and the particular measurements I have in mind aren't unusually difficult or expensive. If it's a null result and--as we suspected--there are no legitimate subgroups, we will not have wasted money that wasn't already earmarked in this direction.
2) In the unlikely event that endogenous antibody glycosylation does strongly predict treatment response in ME/CFS, we are being handed a concrete lead on a silver platter. Per the mechanistic work that I linked earlier, we could design another experiment to confirm that this subgroup response is due to the IVIG's effect on Fc receptor-mediated NFkB signaling suppression in myeloids, which might give us useful information about one possible road to ME/CFS.
That's all I've been saying this whole time, with appropriate skepticism baked in. Bowing out now as I don't speak for ghosts.
@Tyler Hulett hi!
You mentioned looking at specific targets (like MED20) versus broad antibody effects. Do you have any thoughts on whether glycosylation (suggested by @jnmaciuch) could play a role alongside the specific autoantibodies your lab identified?
Sorry if I framed the thought with mistakes in a very amateurish way.
neophyte32
Senior Member (Voting Rights)
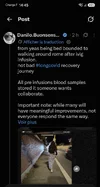
This is already one of several posts from this Italian doctor claiming major improvements in ME/CFS patients treated with IVIG.
Here, the case involves a patient who had been bedridden for years and, after just five sessions, was apparently able to walk again for twenty minutes.
Anyone who knows what very severe ME/CFS is like will understand just how extraordinary (almost unimaginable) such an improvement sounds.
So, is this really credible ? I remain cautious when it comes to this kind of testimony, but what makes it particularly interesting is that this does not seem to be the first time this doctor has reported results like these.

Chandelier
Senior Member (Voting Rights)
Looks very scammy to me:So, is this really credible ? I remain cautious when it comes to this kind of testimony, but what makes it particularly interesting is that this does not seem to be the first time this doctor has reported results like these.
Danilo Buonsenso, MD, PhD, PGDip & MSc (Oxford) – Long Covid The Answers
 longcovidtheanswers.com
Struggling With The Lingering Effects Of Long COVID? We’re Here To Help!
Manage Fatigue, Brain Fog, Dizziness, Pain, Anxiety & Insomnia
Step-by-step detailed guidance for practical management of symptoms
4-Part Course in 35 Languages

Struggling with Long COVID? Take Control with Our 4-Part Recovery Course!
Struggling with the lingering effects of Long COVID? We’re here to help! Manage Fatigue, Brain Fog, Dizziness, Pain, Anxiety & Insomnia Step-by-step detailed guidance for practical management of symptoms4-Part Course in 35 Languages REGISTER NOW If you’re ready to feel like yourself again, this...
longcovidtheanswers.com
" I wanted to let you know that I am in remission after completing your course."
Longhauler