
Cognitive-behavioral therapy for post COVID-19 condition: A pilot randomized controlled trial, 2026, Sauer et al.

SNT Gatchaman

Senior Member (Voting Rights)
Staff member
Cognitive-behavioral therapy for post COVID-19 condition: A pilot randomized controlled trial
Sauer; Bräscher; Germer; Huth; Kolb; Mütze; Witthöft

BACKGROUND
The post COVID-19 condition (PCC) is a disabling condition with urgent need for effective treatments. This pilot randomized controlled trial examined the feasibility and efficacy of a cognitive-behavioral therapy (CBT) for PCC in a parallel-group design.

METHODS
N = 53 individuals with PCC were randomized to CBT (n = 27) or 16-week wait-list control (WLC) condition (n = 26). One participant allocated to WLC was excluded after randomization, resulting in an intention-to-treat (ITT) sample of N = 52 participants (CBT: n = 27, age: M = 48.59, SD = 11.52, 77.8% female; WLC: n = 25, Age: M = 48.44, SD = 9.81, 60% female). CBT comprised eight group and five individual sessions addressing cognitive and behavioral factors of symptom maintenance (treatment duration if completed: M = 14 weeks, SD = 1 week). Primary outcomes included fatigue (FSS), overall somatic symptom burden (PHQ-15), and respiratory and cardiovascular symptoms (SBQ™-LC “Breathing” and “Circulation”), assessed at pre-, post-assessment, and follow-up.

RESULTS
Participants receiving CBT showed a significant medium-sized reduction in fatigue directly after treatment compared to the WLC condition (d = −0.58, p = .045), whereas the WLC group showed a significant increase in overall somatic symptoms (d = 0.60, p = .027). Results for respiratory symptoms were mixed, showing inconsistent patterns across analyses. Retrospectively assessed feasibility and treatment satisfaction were good, with few adverse effects reported.

CONCLUSIONS
This pilot trial suggests the feasibility and preliminary efficacy of CBT for PCC. Larger RCTs with active control groups should confirm these findings.

HIGHLIGHTS
• Pilot RCT supports feasibility and acceptability of CBT for post COVID-19.

• Medium-sized reduction of fatigue directly after CBT in post COVID-19.

• Mixed results in relation to respiratory and cardiovascular symptoms.

Web | DOI | Journal of Psychosomatic Research | Open Access
 
Last edited:
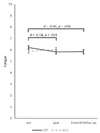
More from the unblinded intervention / subjective outcomes brigade. Credit for not amputating the y-axis but apparently "this pilot RCT indicates that CBT can lead to improvements in fatigue in individuals with PCC, even among those who are severely impaired and show high rates of PEM."


The improvement:

FSS.webp
 
From the introduction —

Fatigue is one of the most common and disabling symptoms of PCC and has been extensively studied in related conditions, such as the chronic fatigue syndrome (CFS), which shows clinical overlap with PCC. Post-exertional malaise (PEM), which is defined as a worsening of symptoms after mild cognitive or physical activity and considered a core criterion […]

In chronic fatigue, research has consistently demonstrated attentional biases towards health-threatening information, increased body focus, illness-related interpretation biases, and broader maladaptive illness perceptions. […] Research additionally suggests that activity-related fears and negative expectations regarding activity are associated with lower mental and physical performance. Reduced activity levels are in turn associated with greater fatigue severity.

[…] highlight the central role of expectations for somatic symptom perception and activity selection. […] consistent with current predictive processing and active inference models of somatic symptom perception. According to these models, persistent somatic symptoms emerge when symptom-related expectations are overly precise and disproportionately affect perception, even in the absence of corresponding physiological dysfunction. […] proposed as transdiagnostic processes underlying a wide range of persistent somatic symptoms.

From this perspective, interventions based on a bio-psycho-social model appear particularly promising. Cognitive-behavioral therapy (CBT) targets both cognitive (e.g., attention, symptom-related cognitions) and behavioral (e.g., avoidance of physical activity) factors and could serve as an effective treatment approach […]
 
From methods —

The eight group and five individual sessions were based on a bio-psycho-social model and comprised cognitive and behavioral elements, including attention flexibility, cognitive restructuring, and modification of maladaptive activity patterns through behavioral experiments.

A stupifyingly large number of questionnaires. All filled in x3: pre, post and three months post.

Primary outcomes comprised somatic symptom distress and related thoughts, feelings, and behaviors. Somatic symptom distress was assessed with the Fatigue Severity Scale (FSS), the Patient Health Questionnaire-15 (PHQ-15), the “Breathing” and “Circulation” scales of the Symptom Burden Questionnaire™ for Long Covid (SBQ™LC), and the Post-Exertional Malaise (PEM) Scale of the DePaul Symptom Questionnaire-2 (DSQ-2). Symptom-related thoughts, feelings, and behaviors were measured with the Somatic Symptom B Criteria Scale (SSD-12).

As secondary outcomes, we assessed depressive symptoms with the Patient Health Questionnaire-9 (PHQ-9), and anxiety symptoms with the Generalized Anxiety Disorder Scale-7 (GAD-7). Illness perceptions were measured with the Brief Illness Perception Questionnaire (B-IPQ) and somatosensory amplification with the Somatosensory Amplification Scale (SSAS). The Work Productivity and Activity Impairment Questionnaire (WPAI) was implemented to assess absenteeism […], presenteeism […], overall work productivity loss, and activity impairment

Adverse effects were assessed with the Inventory for the Assessment of Negative Effects of Psychotherapy (INEP). Treatment satisfaction was measured post-treatment using the Client Satisfaction Questionnaire-8 (CSQ-8), and after every individual or group session with the Session Rating Scale (SRS) and the Group Therapy Session Evaluation Form Patients (GTS-P)

Credibility and expectancy were assessed using the Credibility/Expectancy Questionnaire (CEQ)
 
Last edited:
Discussion —

The sample studied was severely impaired with most participants being on long-term sick leave, fulfilling PEM criteria, and having previously received in-patient rehabilitation.

I feel sorry for these patients.

The results consistently indicated a medium-sized reduction in fatigue during CBT, whereas in the WLC group overall somatic symptom burden worsened. In addition, ANCOVAs revealed medium-sized improvements in respiratory symptoms directly after CBT, although these effects were not confirmed by the MMRMs. Divergent findings between ANCOVAs and MMRMs are most likely attributable to methodological differences regarding model assumptions, handling of missing data, and estimation of effects.

About those model assumptions…

[…] this pilot RCT provides preliminary evidence that CBT may lead to meaningful improvements in fatigue immediately after treatment in individuals with PCC. Given that fatigue is among the most prevalent and disabling symptoms in PCC, this finding is of high clinical relevance. Moreover, the findings align with the results of Kuut and colleagues and with a body of research on the efficacy of CBT and GET in syndromes predominantly characterized by fatigue such as ME/CFS.


Given that more than 90% of participants fulfilled PEM criteria, this study additionally indicates that improvements by CBT, which aims at increasing physical or mental activity, are also possible in people with extended or excessive fatigue after exertion. This finding might help to address ongoing concerns regarding the applicability and negative effects of CBT in individuals with PEM.

It might if you don't understand what PEM is.

However, at the 3-month follow-up, no significant effects on fatigue or other primary outcomes were observed in the ITT sample. Only in the pooled sample, a significant small-sized reduction in fatigue compared to the pre-assessment was seen. […] Overall, these findings point to potential challenges regarding the stability of treatment effects.

"potential challenges regarding the stability of treatment effects" — such as: it doesn't work.

From a clinical perspective, a short-term CBT intervention might be insufficient to ensure sustained improvements in a severely impaired sample of individuals with PCC.

Ah, of course — more needed. That's the ticket.

Extending treatment duration and implementing booster sessions, which was even suggested by some participants, could help to consolidate gains and to better integrate strategies into daily life. Additional approaches, such as peer monitoring by former benefiting participants, digital aftercare interventions, or low-frequency group meetings, could further enhance sustainability of effects.

You should set up some companies to market these ideas.

Regarding PEM, no significant changes were observed in either the ITT or pooled sample (both directly after treatment and at 3-month follow-up). This aligns with previous studies, which also administered the DSQ(−2) PEM and did not observe any improvements after rehabilitation interventions. Both the high prevalence of PEM at pre-assessment in the present (> 90%) and previous studies (72–99%), indicating a left-skewed distribution, and the dichotomization of the originally ordinal items might have limited the sensitivity to change, which has not been validated yet.

That sounds made up.

Beyond methodological reasons, activity resumption may initially have increased PEM in the CBT group, potentially counteracting long-term positive effects. Furthermore, the broad definition of PEM, comprising symptoms occurring more than 24 h (or even longer) after activity, could be inflated by maladaptive attributional processes. Future interventions therefore should more explicitly address negative symptom interpretations and attributions following graded activity increase.

Oh please stop.

In relation to secondary outcomes, no significant effects were observed in the ITT sample immediately after treatment. However, at the 3-month follow-up, small improvements in depressive symptoms (compared to the pre-assessment) were seen.

Just desperation.

no significant effects or even an increase from post-assessment to follow-up in the CBT group were observed for the general activity impairment index (WPAI activity impairment), which assesses limitation in daily activities. It remains unclear whether this finding reflects a true lack or deterioration of functional improvement after CBT or whether the intervention was too short to achieve positive changes in everyday functioning.

Oh definitely the answer is more CBT.

Functional recovery in PCC, in particular regarding work, might require longer treatments and additional support by workplace integration or rehabilitative programs.

Totes.
 
Last edited:
More from the unblinded intervention / subjective outcomes brigade. Credit for not amputating the y-axis but apparently "this pilot RCT indicates that CBT can lead to improvements in fatigue in individuals with PCC, even among those who are severely impaired and show high rates of PEM."


The improvement:

View attachment 33208
We need a name for this genre of plot. I'm sick of seeing them to be honest.
 
Discussion —


I feel sorry for these patients.


About those model assumptions…


It might if you don't understand what PEM is.


"potential challenges regarding the stability of treatment effects" — such as: it doesn't work.


Ah, of course — more needed. That's the ticket.


You should set up some companies to market these ideas.


That sounds made up.


Oh please stop.


Just desperation.


Oh definitely the answer is more CBT.


Totes.
I like your short but poignant comments a lot.

Authors with so much bias against the illness they are supposed to study should leave research immediately.
 
Thanks for the quotes and your comments, @SNT Gatchaman. It's only bearable reading such blinkered nonsense with your asides showing up what crap they are spouting.

This nonsense surely has to stop some time. Health providers surely can't afford to be wasting money putting sick people through ever lengthening ineffective nonsense like this.
 
Worth mentioning that this is the fourth paper I've seen that, in a very heterogeneous long COVID population, has an extraordinary % assessed to have PEM using DSQ PEM metrics. Previously, previously. ~90% of a generic LC cohort having PEM is far higher than could reasonably be expected. I think this is more evidence that those metrics are not really assessing PEM, but perhaps something that correlates with PEM but is far more common such as exertional intolerance.
 
Not a controlled trial, but that aside, doing a feasibility trial for something that has been part of recommendations and guidelines for decades, published in a journal controlled by people who have been involved in making those recommendations and guidelines as they are is pure embarrassment. It's even worse in context, and the more context you add the worse it looks.

It's hard to understand how it's completely impossible to get authorities to give a damn about how this is obviously screwed up, how something that works obviously never needs to do any "uh, is this even possible to use this thing we've been forcing down people's throats for decades?" trial. Which they can't possibly know. They already think it works, despite there being ample conflicting evidence, and yet most trials that get approved are still just mere pilot "preliminary" (postliminary?) spin of the wheel.

There is simply nothing else like it anywhere, and it's completely impossible to stop. In fact, like a malignant cancer, it just keeps growing. This is the most bizarre grift ever. It's truly like a social cancer, it eats up people alive and out the end only spews out another malignant tumor that goes on to do the same.
 
It seems like they had quite a few. primary outcomes. Did they do any correcting for multiple tests? I didn't see it.

Also, can someone explain to me the difference between the ANCOVA findings on the primary outcomes, and the mixed models for repeated measures (MMRM) results? They seem to get different results on those for the PHQ-15 on somatic symptoms--there's no difference in the primary analysis but there is a difference in the MMRM analysis, which was part of sensitivity analysis but is what they mention in the abstract. Also, they refer to the MMRM results as "post-hoc," which I also don't understand.
 
Last edited:
Credibility and expectancy were assessed using the Credibility/Expectancy Questionnaire (CEQ) [59]

[59] is Psychometric properties of the credibility/expectancy questionnaire (2000)

That questionnaire is —

"We would like you to indicate below how much you believe, right now, that the therapy you are receiving will help to reduce your anxiety. Belief usually has two aspects to it: (1) what one thinks will happen and (2) what one feels will happen. Sometimes these are similar; sometimes they are di!erent. Please answer the questions below. In the "first set, answer in terms of what you think. In the second set answer in terms of what you really and truly feel. We do not want your therapist to ever see these ratings, so please keep the sheet covered when you are done."

Set I
  1. At this point, how logical does the therapy offered to you seem?
  2. At this point, how successfully do you think this treatment will be in reducing your trauma symptoms?
  3. How confident would you be in recommending this treatment to a friend who experiences similar problems?
  4. By the end of the therapy period, how much improvement in your trauma symptoms do you think will occur?
Set II
For this set, close your eyes for a few moments, and try to identify what you really feel about the therapy and its likely success. Then answer the following questions.
  1. At this point, how much do you really feel that therapy will help you to reduce your trauma symptoms?
  2. By the end of the therapy period, how much improvement in your trauma symptoms do you really feel will occur?

CEQ.webp


According to that the CBT and Waitlist Controls had similar assessment of the credibility and expectation for their respective treatments prior to. Eg credibility was 7.76±1.18 for CBT and 7.28±0.89 for WLC.

TBM (Truthiness-Based Medicine) I guess.
 
Last edited:
Just reading that questionnaire is messing with my head already. This whole cognitive restructuring process aimed at getting patients to not believe their own symptoms and not to take them seriously is looking increasingly like sinister brainwashing aimed at making sick people never dare mention any symptoms to a doctor again unless they have a rash or a broken bone that shows up on X ray or are bleeding or have a high temperature to prove they are genuinely sick.
 
[59] is Psychometric properties of the credibility/expectancy questionnaire (2000)

That questionnaire is —

"We would like you to indicate below how much you believe, right now, that the therapy you are receiving will help to reduce your anxiety. Belief usually has two aspects to it: (1) what one thinks will happen and (2) what one feels will happen. Sometimes these are similar; sometimes they are di!erent. Please answer the questions below. In the "first set, answer in terms of what you think. In the second set answer in terms of what you really and truly feel. We do not want your therapist to ever see these ratings, so please keep the sheet covered when you are done."

Set I
  1. At this point, how logical does the therapy offered to you seem?
  2. At this point, how successfully do you think this treatment will be in reducing your trauma symptoms?
  3. How confident would you be in recommending this treatment to a friend who experiences similar problems?
  4. By the end of the therapy period, how much improvement in your trauma symptoms do you think will occur?
Set II
For this set, close your eyes for a few moments, and try to identify what you really feel about the therapy and its likely success. Then answer the following questions.
  1. At this point, how much do you really feel that therapy will help you to reduce your trauma symptoms?
  2. By the end of the therapy period, how much improvement in your trauma symptoms do you really feel will occur?

View attachment 33230


According to that the CBT and Waitlist Controls had similar assessment of the credibility and expectation for their respective treatments prior to. Eg credibility was 7.76±1.18 for CBT and 7.28±0.89 for WLC.

TBM (Truthiness-Based Medicine) I guess.
CBT as a self fullfilling prophecy.
All users of these questionaire studied psychology?
Critical thinking overboard.
Philosophy of science is not part of psychology education?

They must be true believers, not scientists.
 
That questionnaire is —

"We would like you to indicate below how much you believe, right now, that the therapy you are receiving will help to reduce your anxiety. Belief usually has two aspects to it: (1) what one thinks will happen and (2) what one feels will happen. Sometimes these are similar; sometimes they are di!erent. Please answer the questions below. In the "first set, answer in terms of what you think. In the second set answer in terms of what you really and truly feel. We do not want your therapist to ever see these ratings, so please keep the sheet covered when you are done."
What a truly bizarre questionnaire. I wouldn't even know what to answer, because the questions are uninterpretable. I don't do beliefs, I don't have any, I find the concept of having beliefs weird. And I certainly would not know how to answer either set of questions. Might as well ask how beige a sound is, or how much roundness defines the saltiness of a piece of food. The questions don't even make sense.

The self-selection effect they create is absurd, it's likely stronger than selecting participants from an astrology conference and asking them about astrology, as if it reflected the whole population. It's beyond blatant that the solution to the bias crisis in this discipline has been to simply stop bothering and just maximize all of them to the most extreme level they can come up with. It's not even subtle anymore.
 
CBT as a self fullfilling prophecy.
All users of these questionaire studied psychology?
Critical thinking overboard.
Philosophy of science is not part of psychology education?

They must be true believers, not scientists.
It's looking more like the opposite to me: this is nihilistic, it believes in nothing at all. They will use any tool, any way they see fit, to get their way. They will cheat to the maximum degree to achieve their ends. It's just naked corruption and fraud, and both definitions of the latter. Most of this stuff is explicitly forbidden, but the rules are loose for interpretation, and there is no oversight at all, so they just enforce whatever they feel will give them the best results.

The starting point of this ideology is lack of belief, after all. It's not the belief itself in what psychosomatic models say, it's the rejection that our experience of reality is just that. Instead all we get is marketing consultant-level of nonsense, "optimizing" products that don't even actually exist but they have secured corrupt government contracts for anyway, guaranteed and safe. The fact that this industry faces zero real pressure to deliver is beyond obvious, they can laze it out, produce nothing and still flourish.
 
Last edited:
Back
Top Bottom